

After a diagnosis of endometrial cancer, the next conversation is usually about staging: how far the cancer has spread and what that means for treatment. Staging is what shapes the plan, which is why your doctor may order further scans before discussing care options with you.
Here’s how endometrial cancer is staged, the treatments used at each stage, from surgery to radiotherapy, chemotherapy, and hormonal therapies, and the factors your care team weighs up when putting a treatment plan together.
How is endometrial cancer staged?
Endometrial cancer is staged based on how far the cancer has grown and whether it has spread beyond the uterus. Staging helps doctors understand the extent of the disease and plan the most appropriate treatment. A higher stage generally indicates that the cancer has spread further and may require more intensive or combined treatments.
A gynaecology specialist will determine the stage using a combination of diagnostic tests and findings from surgery, which include:
Biopsy:
A small sample of tissue is taken from the endometrium, the inner lining of the uterus, and then examined under a microscope by a pathologist.
This procedure confirms whether cancer cells are present and helps identify the type and grade of the cancer.
Lymph node assessment:
During surgery, your doctor may remove or sample nearby lymph nodes to check whether the cancer has spread beyond the uterus.
The presence of cancer cells in the lymph nodes can affect the cancer stage and influence whether additional treatment is recommended.
Imaging tests:
Once your doctor confirms endometrial cancer, they may recommend imaging tests to assess the size and location of the tumour. These tests can also check whether the cancer has spread beyond the uterus.
Depending on your individual conditions, these may include CT scans, MRI scans, PET scans, and chest X-ray tests.
Blood tests:
A blood test may be used to assess your general health and check how well your liver and kidneys are functioning. Your doctor may also recommend a CA-125 blood test in certain situations, although this marker alone cannot confirm whether uterine cancer has spread.
What are the stages of endometrial cancer?
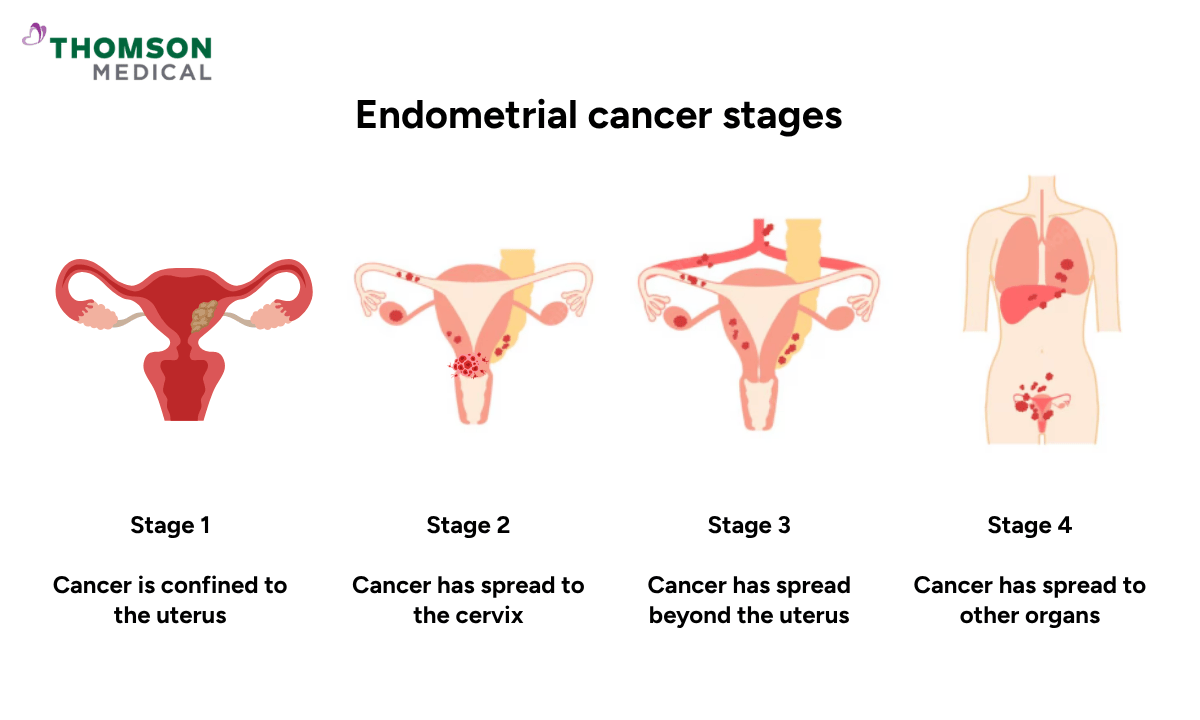
There are four staging systems of endometrial cancer, based on how far the cancer has spread and which parts of the body are affected.
Stage 1:
The cancer is confined to the uterus and has not spread to nearby lymph nodes or distant organs. It may be limited to the endometrium, the inner uterine lining of the uterus, or may have grown deeper into the myometrium, the muscular layer of the uterus.
Stage 2:
The cancer has spread from the uterus into the connective tissue of the cervix, known as the cervical stroma, but remains within the uterus and cervix.
Stage 3:
The cancer has spread beyond the uterus but remains in nearby areas of the pelvis or abdomen. It may affect the ovaries, fallopian tubes, vagina, surrounding tissues, or nearby lymph nodes.
Stage 4:
The cancer has spread beyond the pelvic region. It may affect nearby organs such as the bladder, bowel, or more distant parts of the body, including the lungs, liver, or bones, as well as distant lymph nodes.
Endometrial cancer treatment options by stage
The treatment options for endometrial cancer depend on the stage, as well as its type, grade, and your overall health. Some treatments aim to remove the cancer, while others help reduce the risk of recurrence or control of cancer that has spread to other parts of the body. The following are some of the treatment options available:
Surgery
Surgery is the main treatment for many women with early-stage endometrial cancer, particularly stage 1 and stage 2 disease. The most common procedure is a hysterectomy, which removes the uterus and cervix (total hysterectomy), often together with the fallopian tubes and ovaries. Nearby lymph nodes may also be assessed or removed to check whether the cancer has spread.
Surgery may also be considered for some women with stage 3 or stage 4 cancer if the tumour can be safely removed. Your specialist will assess whether surgery is suitable based on where the cancer has spread and whether removing the tumour is likely to improve cancer control.
Radiotherapy
Radiotherapy, also known as radiation therapy, uses high-energy radiation to destroy cancer cells. This may include external beam radiotherapy or vaginal brachytherapy. It may be recommended after surgery for some women with stage 1 or stage 2 cancer who have a higher risk of the cancer returning.
For stage 3 or stage 4 disease, radiotherapy may be used to control cancer in specific areas, reduce tumour growth, or relieve symptoms such as pain or bleeding. It may also be considered when surgery is not possible.
Chemotherapy
Chemotherapy uses anti-cancer medicines that travel throughout the body to destroy cancer cells. It is more commonly used for stage 3, stage 4, or recurrent endometrial cancer, particularly when there is a higher risk that the cancer has spread or may return.
Depending on your individual condition, chemotherapy may be given before or after surgery, alongside radiotherapy, or as part of treatment for advanced cancer. The specific medicines and number of treatment cycles will depend on your overall health.
Hormone therapy
Hormonal therapy may be considered as a fertility preservation option for younger women with low-grade or early-stage endometrioid cancer who wish to have children in the future. Progestin-based treatment may help control or shrink the cancer while preserving the uterus, but it requires close monitoring and is not suitable for everyone.
Hormonal therapy may also be considered for advanced or recurrent endometrial cancer (stage 3 or 4) when the cancer is hormone-sensitive, particularly if it has specific hormone receptors such as progesterone receptors. It may be used when other treatments are not suitable or to help control slower-growing cancer.
Immunotherapy
Immunotherapy is mainly considered for advanced, metastatic, or recurrent endometrial cancer, which may include stage 3 or stage 4 disease. Depending on the cancer's characteristics and previous treatments, immunotherapy may be used alone or combined with other treatments. Your specialist may recommend further testing to determine whether immunotherapy is appropriate for your cancer.
Targeted therapy
Targeted therapy is generally considered for advanced or recurrent endometrial cancer, particularly stage 3 or stage 4 disease, when the cancer has genetic changes that can be targeted with available medicines.
The type of targeted therapy offered depends on the tumour's molecular profile and previous treatments. It may be used alone or in combination with other treatments to help control the cancer and slow its growth.
If you are unsure which treatment may be suitable for your condition, consult with a specialist to help you make a more informed decision about your care. Schedule an appointment with Thomson Women's Clinic & Cancer Surgery for a consultation with our gynaecological oncologist.
Our women's cancer specialist
Loading...
Endometrial cancer survival rates by stage
When discussing endometrial cancer outcomes, you may come across the term survival rates. While the word “survival” can feel worrying, these figures are not meant to predict how long an individual person will live or what their outcome will be after diagnosis.
Rather, they provide the percentage of people with a particular cancer who are alive five years after diagnosis, compared to people of the same age in the general population without that cancer.
They can help doctors to understand the overall effectiveness of available treatments. The five-year period is also considered meaningful for assessing cancer outcomes, as recurrences are likely to occur within this timeframe.
Based on the research performed in the US, which analysed over 129,000 patients using the FIGO 2023 staging of endometrial cancer, the estimated 5-year outlook varies according to the stage of cancer.
Stage 1:
As the cancer remains within the uterus at this stage, it is generally associated with a more favourable outlook compared with later stages. The estimated 5-year outlook for stage 1 endometrial cancer is around 86% to 88%.
Stage 2:
At this stage, the cancer has extended beyond the uterine lining but remains within the reproductive organs; treatment may involve a combination of approaches depending on the cancer characteristics and individual health factors. The estimated 5-year outlook for stage 2 endometrial cancer is around 75% to 85%.
Stage 3:
The cancer has spread beyond the uterus, which may require more comprehensive treatment approaches. The estimated 5-year outlook for stage 3 endometrial cancer is approximately around 41% to 62%.
Stage 4:
As the cancer has spread more extensively, treatment focuses on managing the disease, controlling symptoms, and improving quality of life. The estimated 5-year outlook for stage 4 endometrial cancer is approximately 18% to 33%.
How to manage your health after treatment?

Recovering after endometrial cancer treatment involves more than healing from surgery or completing your treatment. You could help support your recovery and overall wellbeing by:
Following your post-surgery care instructions to support healing and reduce the risk of complications.
Attending regular follow-up appointments so your specialist could monitor your recovery and check for any signs of recurrence.
Reporting new or unusual symptoms promptly to your specialist for further assessment.
Staying physically active once your doctor confirms that it is safe for you to exercise.
Maintaining a healthy lifestyle by eating a balanced diet and following other healthy habits.
If you have any concerns about your recovery or are looking for ongoing care for endometrial cancer after treatment, consult a specialist who could support you through your next steps. Schedule an appointment with Thomson Medical.
FAQ
What is the most common age for endometrial cancer?
Endometrial cancer is most commonly diagnosed in women between the ages of 55 and 64 years, with the average age at diagnosis being around 60 years. Although it predominantly affects women after menopause, it can occasionally occur in younger women, particularly those with inherited genetic conditions or certain hormonal and metabolic risk factors.
How quickly can endometrial cancer spread?
How quickly uterine cancer spreads can vary widely from woman to woman, and there is no fixed timeline for its progression. Factors such as the tumour grade and the cancer type influence the risk and speed of spread. Higher‑grade tumours are generally more aggressive, more likely to spread, and carry a higher risk of metastasis.
Uterine cancers are also grouped into type 1 and type 2 based on how they develop and behave. Type 1 cancers, which are usually low‑grade endometrioid tumours, tend to grow more slowly and often develop over several months or years.
While type 2 cancers, such as papillary serous carcinoma and clear cell carcinoma, are less common but more aggressive. They spread faster beyond the uterus and into lymph nodes or distant organs.
How do you know if endometrial cancer has spread?
The symptoms of endometrial cancer spreading can vary depending on where the cancer has grown. If it remains in or near the uterus, you may experience abnormal vaginal bleeding, unusual discharge, pelvic pain or pressure, pain during urination or intercourse, unexplained weight loss, or persistent tiredness.
If the cancer spreads to other parts of the body, symptoms may depend on the affected organ. These can include changes in urination or bowel movements, abdominal pain, persistent cough or shortness of breath, ongoing bone pain, or headaches and changes in balance, speech, or memory.
However, as these symptoms can also have other causes, your doctor may recommend imaging tests or a biopsy to confirm whether the cancer has spread.
What are the possible complications of endometrial cancer?
When diagnosed and treated at an early stage, endometrial cancer generally responds well to treatment. However, if left untreated or diagnosed at a more advanced stage, complications may occur, including:
- Spread of the cancer to nearby organs or distant metastasis to other parts of the body.
- Anaemia, which may develop due to prolonged or heavy vaginal bleeding.
The information provided is intended for general guidance only and should not be considered medical advice. For personalised recommendations and advice based on your individual circumstances, schedule an appointmentwith Thomson Medical.
References
Mager, K. L., McLean, K. (2026). Endometrial cancer: A review. JAMA, 335(18), 1616-1627. https://doi.org/10.1001/jama.2026.2248
Berek, J. S., Matias-Guiu, X., Creutzberg, C., Fotopoulou, C., Gaffney, D., Kehoe, S., Lindemann, K., Mutch, D., Concin, N. (2023). FIGO staging of endometrial cancer: 2023. International Journal of Gynaecology Obstetrics, 162(2), 383–394. https://doi.org/10.1002/ijgo.14923
For more information, contact us:
Thomson Medical Concierge
- 8.30am - 5.30pm
- WhatsApp: 9147 2051
Need help finding the right specialist or booking for a group?
Our Medical Concierge is here to help you. Simply fill in our form, and we'll check and connect you with the right specialist promptly.
Notice:
The range of services may vary between Thomson clinic locations. Please contact your preferred branch directly to enquire about the current availability.
Get In Touch