

Adenomyosis and endometrial cancer both affect the uterus (womb) and can cause heavy bleeding and pelvic pain, which is why the two are often confused with each other. Adenomyosis is a benign condition in which endometrial tissue grows into the muscular wall of the womb, often causing heavy, painful periods during the reproductive years. Endometrial cancer is a malignant growth that begins in the lining of the womb, and it most often appears after menopause.
Here’s how adenomyosis and endometrial cancer differ in their risk factors, symptoms, diagnosis, and treatment.
What is adenomyosis?
Adenomyosis is a non-cancerous condition that occurs when tissue that normally lines the inside of the uterus (the endometrium) grows into the muscle of the uterus (the myometrium). Although this tissue is in the wrong place, it still responds to the body's monthly hormonal changes by thickening and bleeding during each menstrual cycle.
Unlike the normal uterine lining, this condition makes the blood unable to leave the body because it becomes trapped within the uterine muscle. This can cause the uterus to become enlarged, inflamed, and painful, leading to symptoms that may negatively affect your daily activities.
What is endometrial cancer?
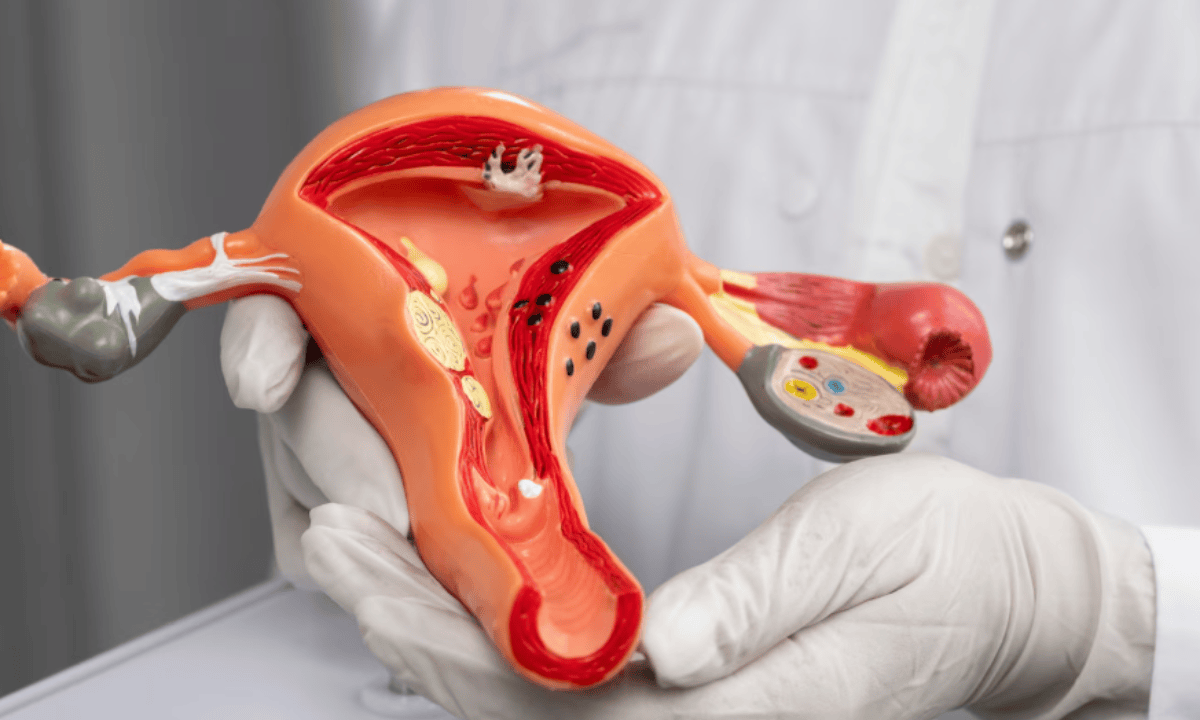
Endometrial cancer is a type of gynaecological cancer that develops in the endometrium, the inner lining of the womb. It is one of the most common gynaecological cancers and typically occurs after menopause, though it can also affect younger women.
Although this cancer is often referred to as uterus or uterine cancer, the two terms are not exactly the same. Uterus cancer is a broader term that describes cancers originating in the uterus, including endometrial cancer and the much rarer uterine sarcoma, which develops in the muscle or supporting tissues of the uterus.
Differences between adenomyosis and endometrial cancer
Adenomyosis and endometrial cancer are two different conditions that can sometimes be confused. The table below outlines the key differences between adenomyosis and endometrial cancer, including their risk factors and symptoms.
| Adenomyosis | Endometrial cancer | |
|---|---|---|
Risk factors | Adenomyosis is commonly diagnosed in women aged 40 to 50 or younger with heavy menstrual bleeding or painful periods. Other factors that can increase the risk include:
| Endometrial cancer is more common after menopause, with the average age of diagnosis around 60. Factors that may increase the risk include:
|
Symptoms | Common symptoms of adenomyosis include:
| Endometrial cancer symptoms include:
|
If you have any of the risk factors mentioned above or are experiencing the associated symptoms, you may consider consulting a doctor for an assessment. Schedule an appointment with Thomson Medical.
Our gynaecological oncologist specialist
Loading...
How are adenomyosis and endometrial cancer diagnosed?
The diagnosis process for adenomyosis and endometrial cancer involves reviewing your symptoms, medical history, and overall health. Your doctor may recommend a combination of physical examinations, imaging tests, and, in some cases, tissue sampling to identify the cause of your symptoms and confirm the diagnosis.
Common diagnostic methods for adenomyosis and endometrial cancer include:
Pelvic examination:
During a pelvic examination, your doctor will assess the vagina, cervix, uterus, and surrounding pelvic areas for any unusual changes, such as tenderness, swelling, an enlarged uterus, or other abnormalities that may require further evaluation.
Transvaginal ultrasound:
A transvaginal ultrasound imaging test uses a small ultrasound probe inserted into the vagina to create detailed images of the uterus.
It is typically the first imaging test used to evaluate suspected adenomyosis and to assess the endometrial lining when endometrial cancer is a concern.
It can show changes such as thickening of the uterine lining, enlargement of the uterus, or other abnormalities that may need further investigation.
Magnetic resonance imaging (MRI):
An MRI scan provides detailed images of the uterus and surrounding tissues.
Your doctor may recommend an MRI if ultrasound findings are unclear, to better characterise adenomyosis within the uterine muscle, or in confirmed endometrial cancer to assess how far the cancer has spread within the uterus.
Endometrial biopsy:
An endometrial biopsy involves collecting a small sample of tissue from the lining of the uterus for examination under a microscope.
It is the main test used to diagnose or confirm endometrial cancer by checking for abnormal or cancerous cells.
Endometrial biopsy is not usually needed to confirm adenomyosis, which is typically diagnosed based on imaging findings.
Hysteroscopy:
During a hysteroscopy, your doctor inserts a thin, lighted instrument called a hysteroscope through the vagina and cervix to examine the inside of the uterus.
This allows direct visual assessment of the uterine lining. If any abnormal areas are found, a tissue sample may be collected for further testing.
Dilatation and curettage (D&C):
A D&C involves gently widening the cervix and removing a sample of tissue from the uterine lining.
Your doctor may recommend a D&C if an endometrial biopsy does not provide enough tissue or if further examination is needed to diagnose or rule out endometrial cancer.
D&C is not routinely used to diagnose adenomyosis but may incidentally reveal it on tissue analysis.
Treatment options
The treatment approach for adenomyosis and endometrial cancer is different because these conditions develop in different ways and affect the uterus differently.
For adenomyosis
Treatment for adenomyosis focuses on relieving symptoms and improving quality of life, with the approach depending on symptom severity and fertility plans. Treatment options may include:
Pain relief medications:
Non‑steroidal anti‑inflammatory drugs (NSAIDs), such as ibuprofen or naproxen, may help reduce menstrual cramps and pelvic pain associated with adenomyosis.
Hormonal treatments:
Hormonal medications, including combined birth control pills, progestin‑based treatments, or a levonorgestrel‑releasing hormonal intrauterine device (IUD).
These treatments may help regulate bleeding and reduce symptoms by thinning the uterine lining and stabilising hormone levels.
Non‑hormonal medications:
Non‑hormonal medicines such as tranexamic acid may be recommended to reduce heavy menstrual bleeding during periods.
Adenomyomectomy:
An adenomyomectomy is a surgical procedure that removes areas of adenomyosis from the uterine muscle while preserving the uterus.
It may be considered for women who wish to maintain their fertility, although suitability depends on individual factors such as the extent and location of adenomyosis and overall uterine health.
For endometrial cancer
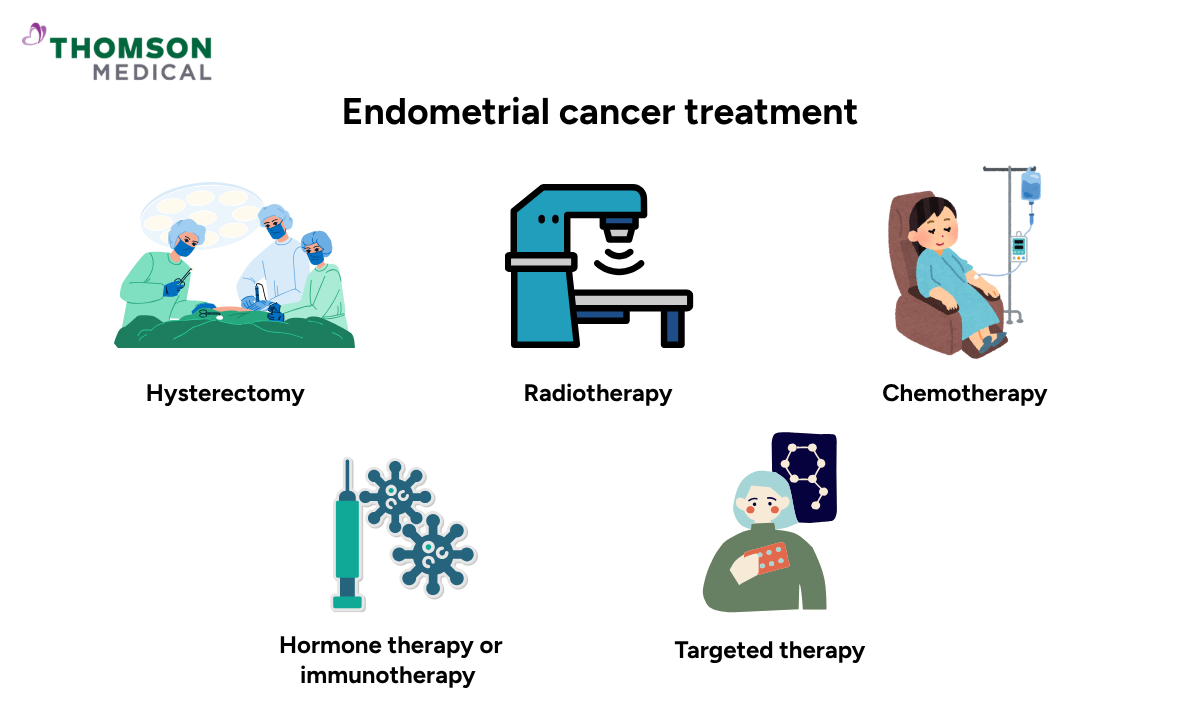
Treatment for endometrial cancer depends mainly on the stage, type, and characteristics of the cancer, as well as your overall health. Treatment options may include:
Hysterectomy:
Hysterectomy is the main surgical treatment for endometrial cancer, especially when the cancer is diagnosed at an early stage and remains within the uterus.
The primary aims of surgery are to remove the cancer and to assess whether it has spread (metastasised) to nearby tissues or lymph nodes.
Radiotherapy:
Radiotherapy is a cancer treatment that utilises high‑energy radiation to destroy cancer cells, reduce the risk of the cancer recurring, or control cancer in specific areas such as the pelvis or vaginal vault (the upper part of the vagina that surrounds the cervix).
Chemotherapy:
Anti‑cancer medicines that travel through the bloodstream to destroy cancer cells that may have spread beyond the uterus or to treat higher‑risk or recurrent cases.
Hormone therapy:
Hormone therapy may be suitable for certain endometrial cancers that respond to hormones.
It can provide a temporary alternative to hysterectomy for women who wish to preserve their fertility.
Immunotherapy:
This treatment works by helping the immune system recognise and attack cancer cells. This treatment may be recommended for some patients with advanced, recurrent, or metastatic endometrial cancer.
Targeted therapy:
This treatment uses medicines that target specific genes that enable cancer cells to grow and survive.
These drugs are usually offered to selected patients with advanced or recurrent disease, often in combination with other cancer treatments
For higher or advanced stages of endometrial cancer, treatment is often more complex. It typically involves a combination of surgery, radiotherapy, chemotherapy, hormone therapy, or newer options such as immunotherapy or targeted therapy.
If you are unsure which treatment may be suitable for your condition, consult with a specialist to help you make a more informed decision about your care. Schedule an appointment with Thomson Women's Clinic for a consultation with a gynaecologist.
What are the potential complications of each condition?
Although adenomyosis and endometrial cancer are different conditions, both can lead to complications. But the type of complications depends on how the condition develops and how it affects the uterus and surrounding tissues.
Complications of adenomyosis
Adenomyosis is not cancer and does not spread to other parts of the body. However, symptoms may become more severe over time. Potential complications include:
Iron-deficiency anaemia: which may develop due to heavy or prolonged menstrual bleeding, that can cause symptoms such as fatigue, weakness, dizziness, or shortness of breath.
Chronic pelvic pain: which may occur due to severe menstrual cramps and ongoing discomfort, affecting daily activities, sleep, emotional wellbeing, and overall quality of life.
Fertility difficulties: which may occur due to changes in the uterus that can make it more challenging to conceive or carry a pregnancy and may increase the risk of miscarriage or certain pregnancy complications.
Complications of endometrial cancer
When diagnosed and treated at an early stage, endometrial cancer generally responds well to treatment. However, if left untreated or diagnosed at a more advanced stage, complications may occur, including:
Spread of the cancer to nearby organs or distant metastasis to other parts of the body.
Anaemia, which may develop due to prolonged or heavy vaginal bleeding.
How to prevent adenomyosis and endometrial cancer?
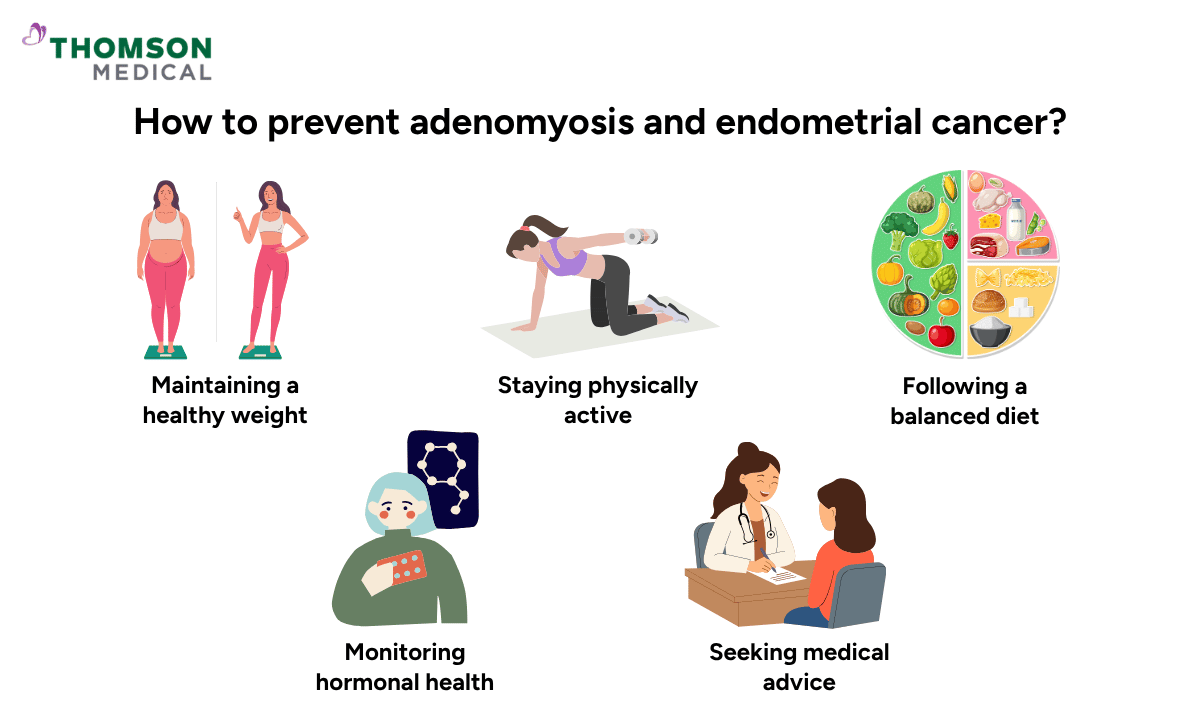
There is currently no guaranteed way to prevent adenomyosis or endometrial cancer completely. However, maintaining a healthy lifestyle and being aware of changes in your body may help reduce certain risk factors and support early detection.
Some steps that may help include:
Maintain a healthy weight: as excess body weight can affect hormone levels, particularly oestrogen, which may influence the risk of endometrial cancer and overall hormonal balance.
Stay physically active: regular exercise can support overall health, help maintain a healthy weight, and is associated with a lower risk of endometrial cancer.
Follow a balanced diet: include a variety of fruits, vegetables, whole grains, and other nutrient-rich foods as part of an overall healthy lifestyle.
Monitor your hormonal health: especially if you experience symptoms such as irregular periods or heavy menstrual bleeding, or if you have conditions such as PMOS.
Additionally, seek medical advice for any unusual symptoms, as early assessment can help identify conditions that require further evaluation.
FAQ
Can you have adenomyosis and endometrial cancer at the same time?
Yes, although it is uncommon, adenomyosis and endometrial cancer can occur at the same time. However, having adenomyosis does not mean that you will have cancer, but any new or unusual symptoms, such as bleeding after menopause or changes in your usual menstrual pattern, should be assessed by a doctor.
Can adenomyosis be mistaken for endometrial cancer?
Adenomyosis and endometrial cancer can sometimes be difficult to distinguish because they may cause similar symptoms, such as heavy menstrual bleeding, pelvic pain, or abnormal bleeding.
However, they are different conditions that develop in different parts of the uterus. Doctors may use a combination of pelvic examinations, imaging tests, and, when needed, a biopsy to determine the correct diagnosis.
Can adenomyosis turn into cancer?
No, adenomyosis does not turn into endometrial cancer. Adenomyosis is a non-cancerous condition and is not considered a precancerous condition. However, because some symptoms may overlap with endometrial cancer, seeking medical advice is important for an accurate diagnosis.
Does adenomyosis increase the risk of developing endometrial cancer?
Current evidence does not show that adenomyosis directly causes endometrial cancer or significantly increases the risk of developing it. Both conditions affect the uterus but develop through different processes. Regular medical follow-up can help identify any concerning symptoms early, especially for women with risk factors for endometrial cancer.
The information provided is intended for general guidance only and should not be considered medical advice. For personalised recommendations and advice based on your individual circumstances, schedule an appointment with Thomson Medical.
For more information, contact us:
Thomson Medical Concierge
- 8.30am - 5.30pm
- WhatsApp: 9147 2051
Need help finding the right specialist or booking for a group?
Our Medical Concierge is here to help you. Simply fill in our form, and we'll check and connect you with the right specialist promptly.
Notice:
The range of services may vary between Thomson clinic locations. Please contact your preferred branch directly to enquire about the current availability.
Get In Touch